
Your clinical AI is only as good as the data it can reach. That sounds obvious, but EHR interoperability challenges tend to show up quietly, in the gap between data being sent and data being understood. If you're building or assessing AI-powered workflows, knowing where that gap lives and how to close it matters more than most deployment guides let on.
TLDR:
- EHR interoperability means two systems can exchange data and interpret it the same way, a distinction most deployments fail to meet.
- The four levels of interoperability range from foundational (data transfer only) to organizational (legal agreements in place), and clinical AI stalls at the semantic and organizational layers most often.
- Semantic gaps are the hardest problem for AI: a lab result coded differently across two source systems can produce the wrong output with no error flagged.
- Write access to EHRs requires separate vendor credentialing and contractual terms, which is why most AI deployments stop at surfacing recommendations instead of taking real actions.
- Concurrence audits read and write constraints before scoping any AI-powered workflow, with native integrations across Epic, Oracle Health, and Athenahealth and over 10 million patient interactions completed at a 100% safety record.
What Is EHR Interoperability?
EHR interoperability is the ability of different electronic health record systems to exchange patient data with each other and actually do something useful with it. That last part matters: two systems can technically share a file and still fail to interpret it the same way, leaving clinicians no better off than before.
In practice, a primary care physician in one network can pull up a patient's hospital discharge notes from a different system, or a care coordinator can see lab results ordered by a specialist they have never met. The data moves across organizational and technical boundaries without someone manually re-entering it or sending a fax.
A patient's health history rarely lives in one place. They change insurers, move cities, see multiple specialists, and visit urgent care when their usual provider is unavailable. Without interoperability, each encounter starts with an incomplete picture, and clinicians make decisions based on whatever partial record they have on hand.
The Four Levels of EHR Interoperability
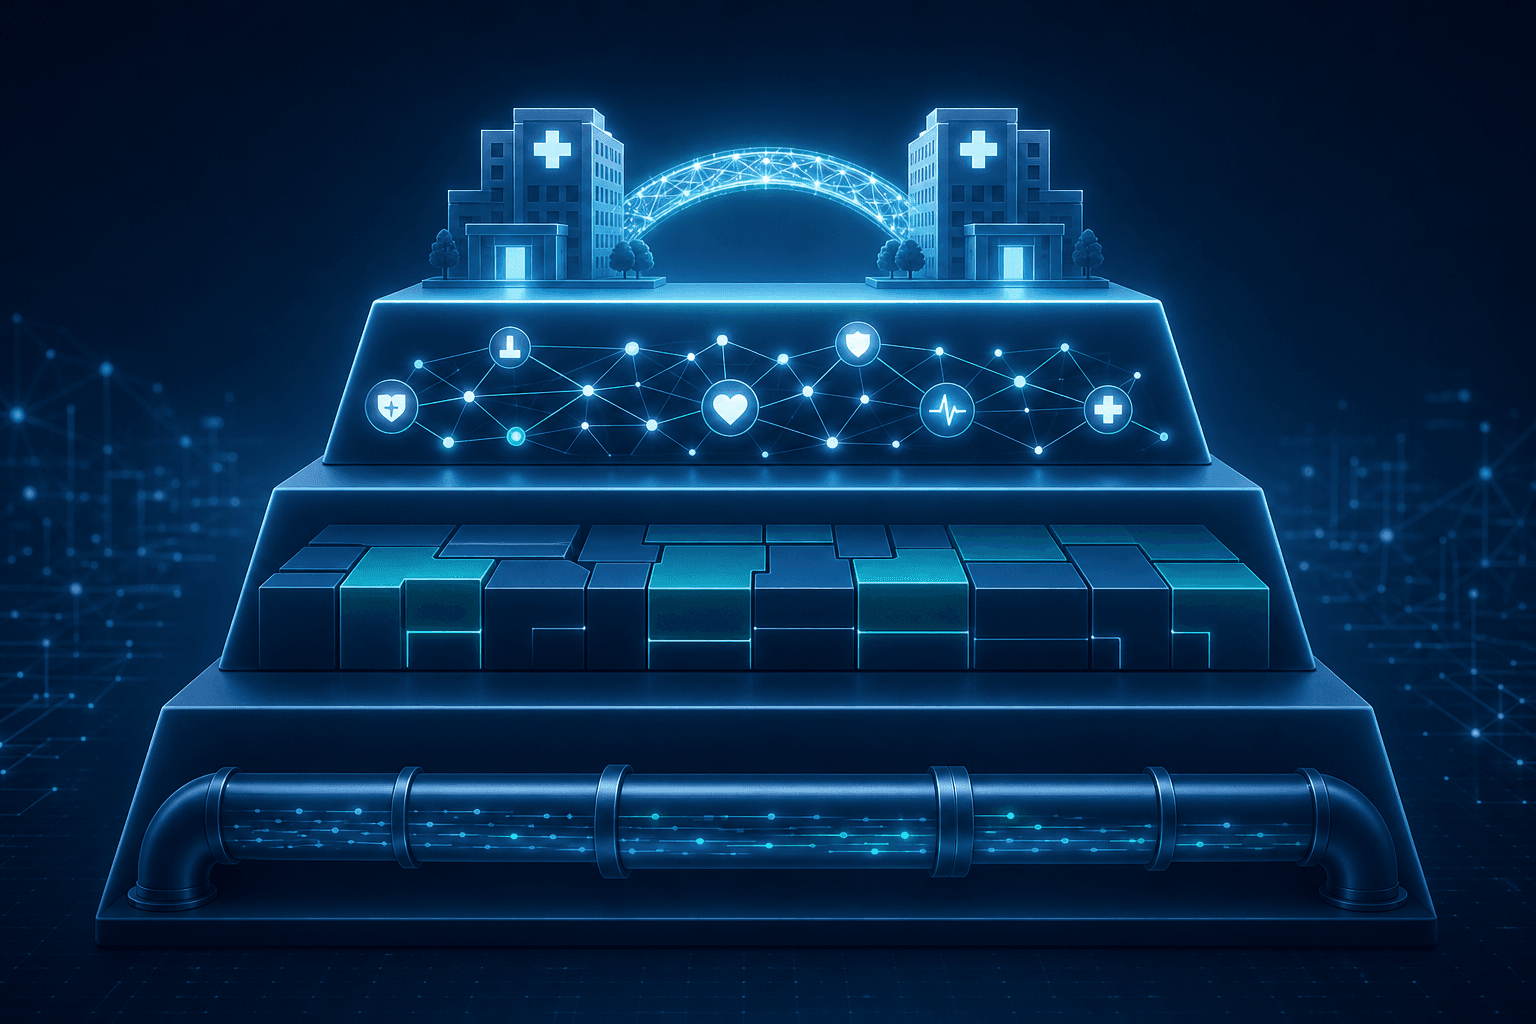
The four levels form a progression, and knowing where your systems sit on that progression tells you a lot about what your AI deployment can actually do.
Foundational
The baseline: two systems can send and receive data with no requirements around format or meaning. Data arrives at the right destination, and that is the extent of the guarantee.
Structural
Data is formatted consistently so the receiving system can parse it. HL7 and FHIR messages fall here. Whether the receiving system interprets a field the same way the sending system intended it is a separate question.
Semantic
Both systems share the same meaning for the data they exchange. A diagnosis code, a medication name, a lab result each mean the same thing on both ends, requiring shared vocabularies like SNOMED CT, LOINC, and RxNorm. Most deployments stall here because aligning two organizations on terminology across years of legacy data is genuinely hard work.
Organizational
The governance layer. Policies, legal agreements, and workflows are in place so data can flow across institutions, technically and legally. TEFCA sits at this level.
For AI, semantic and organizational interoperability are where the real friction lives. A model receiving structurally valid but semantically inconsistent data will produce unreliable outputs, often without flagging that anything went wrong. That is why Concurrence built the Health World Model as a unifying layer.
Key Standards and Frameworks
Several standards govern how health data moves between systems, and they operate at different layers. Understanding what each one actually does prevents the common mistake of treating them as alternatives to one another.
HL7 v2 is the workhorse of hospital messaging, in production use since the late 1980s, handling high-volume transactional messages most EHRs still run on: lab orders, ADT notifications, pharmacy updates. Its ubiquity is both its strength and its limitation, because implementations vary widely by vendor, so two systems both running HL7 v2 can still require custom translation work to communicate reliably.
EHR Interoperability Standards at a Glance
| Standard | Interoperability Layer | Primary Function | Key Limitation |
|---|---|---|---|
| HL7 v2 | Structural | High-volume transactional messaging (lab orders, ADT notifications, pharmacy updates) | Vendor implementations vary widely; custom translation often still required |
| C-CDA | Structural | Standardizes complete clinical documents (discharge summaries, referral notes) for exchange | Document-level only; does not govern real-time data queries |
| USCDI | Structural / Semantic | Federally defined data classes and elements that certified EHRs must be capable of exchanging | Specifies what data is in scope; relies on other standards for how it moves |
| FHIR R4 | Structural / Semantic | API-based real-time data exchange; foundation for payer APIs, patient access mandates, and AI integrations | Adoption of write scopes and semantic value sets remains uneven across vendors |
| TEFCA | Organizational | Trust framework and legal agreements that support cross-institutional data exchange | Adoption across care settings remains uneven |
The Standards Stack
- C-CDA (Consolidated Clinical Document Architecture) standardizes how complete clinical documents are structured for exchange, covering discharge summaries and referral notes. It sits above HL7 v2 and focuses on document-level transfers.
- USCDI (United States Core Data for Interoperability) is a federally defined set of data classes and elements that certified EHR systems must be capable of exchanging. It specifies what data is in scope; the other standards govern how it moves.
- FHIR (Fast Healthcare Interoperability Resources) is the API-focused standard maintained by HL7 for real-time data exchange. In April 2025, the FDA formally opened a public docket reviewing FHIR for real-world data submissions, a signal that its reach is extending beyond clinical exchange into regulatory evidence.
- TEFCA operates at the organizational level, providing the trust framework and legal agreements that allow data to cross institutional boundaries once the technical pieces are in place.
The CMS Promoting Interoperability Program
The CMS Promoting Interoperability Program traces its roots to the HITECH Act of 2009, which created financial incentives for hospitals and physicians to adopt and "meaningfully use" certified EHR tech. MACRA later sunset the Medicare EHR Incentive Program for eligible clinicians and folded similar requirements into MIPS as one of four scored performance categories.
Today the program works as a compliance obligation with direct payment consequences, similar in spirit to the CMS ACCESS Model that institutions must now comply with. As outlined by CMS for the 2026 reporting year, eligible hospitals and critical access hospitals must submit electronic clinical quality measure data, complete required attestations, and earn a minimum total score within CMS collection timelines. Failing to do so triggers a downward payment adjustment.
That payment pressure shapes which EHR data exchange investments get funded, in what order, and what level of data fidelity leadership will accept before signing off, pressure that has helped drive new clinical AI funding toward solving the problem.
Real-World Examples of EHR Interoperability
Interoperability looks different depending on where in the care journey it happens. A few concrete cases show the range.
A patient discharged from a hospital after a cardiac event arrives at their primary care follow-up appointment. If the hospital and clinic share connectivity through a health information exchange, the physician pulls the discharge summary, medication reconciliation, and procedure notes directly into their EHR before the patient sits down. No phone calls to medical records, no gaps filled by whatever the patient remembers.
On the payer side, prior authorization requests increasingly run through FHIR-based APIs that query a provider's EHR directly. The payer system retrieves relevant clinical data, applies coverage logic, and returns a decision within the same workflow. The process is still imperfect at scale, but the direction is toward bidirectional automation in place of manual document exchange.
Public health reporting offers a third scenario. Reportable conditions can be pushed automatically from a certified EHR to state and local health agencies, replacing manual reporting that historically created lag in surveillance data.
Each case sits at a different level of technical maturity. The discharge summary exchange might rely on a document pull with limited semantic alignment. The prior auth API depends on FHIR R4 and shared value sets. The public health feed requires both structural and semantic agreement to be useful. The gap between "data was sent" and "data was understood" is where most implementations run into trouble.
Benefits of EHR Interoperability
As of 2024, 99% of hospitals have adopted certified EHRs. The records exist. The question is whether they travel.
When they do, the benefits are concrete:
- Reduced duplicate testing. A clinician who can see a recent CT scan ordered by another provider skips reordering it, saving cost and sparing the patient a second round of contrast dye.
- Fewer care gaps from hand-offs. Discharge summaries, medication lists, and pending referrals that arrive automatically at the next provider reduce the chance something important gets missed in transition.
- Faster clinical decisions. Pulling a complete medication history through a connected system takes seconds. Waiting for records by fax can take days, and decisions often can't wait.
- Better patient safety. Allergy lists and active prescriptions that don't follow a patient across systems create real medication risks. Interoperability brings those facts to the point of care before a decision is made.
Each benefit depends on exchange quality as much as adoption, which is part of why a unified clinical AI platform matters. A hospital with a certified EHR that shares data at only the foundational level captures almost none of these gains. The value scales with how much the receiving system can actually do with what it receives.
Barriers to EHR Interoperability
High EHR adoption rates don't translate automatically into functional data exchange. The OECD's 2026 health working paper on interoperability discusses persistent interoperability barriers that remain even where EHR adoption is high.
One of the most common barriers is vendor-specific data modeling. Major EHR vendors implement shared standards differently, often extending them with proprietary fields, custom code sets, or non-standard workflows, so two certified systems can still require substantial translation work before their outputs align.
Semantic inconsistencies compound the problem. Clinical concepts are frequently coded differently across organizations, with lab units, medication codes, and diagnosis hierarchies failing to map cleanly. A 2024 systematic review in JMIR Medical Informatics identified semantic interoperability as one of the primary unresolved challenges in EHR systems, with no single approach yet proving sufficient at scale.
Information blocking, while formally prohibited under the 21st Century Cures Act, still surfaces through pricing structures, restrictive API terms, and interface fees that can make data access costly for smaller institutions. Governance gaps create a parallel problem. Even when two systems can technically exchange data, the legal agreements needed to authorize that exchange across organizational boundaries are often absent, which is one reason some institutions look at Health World Models built on Databricks for a more unified data foundation. TEFCA was designed to close this gap, but adoption across care settings remains uneven.
How EHR Interoperability Affects Clinical AI Deployment
Clinical AI runs on context. When a workflow needs to assess care gaps, flag a drug interaction, or route someone to the right level of care, it draws on whatever data it can actually reach. If that data is incomplete or siloed behind a system that won't share it, the AI reasons from a partial picture, and its outputs reflect that.
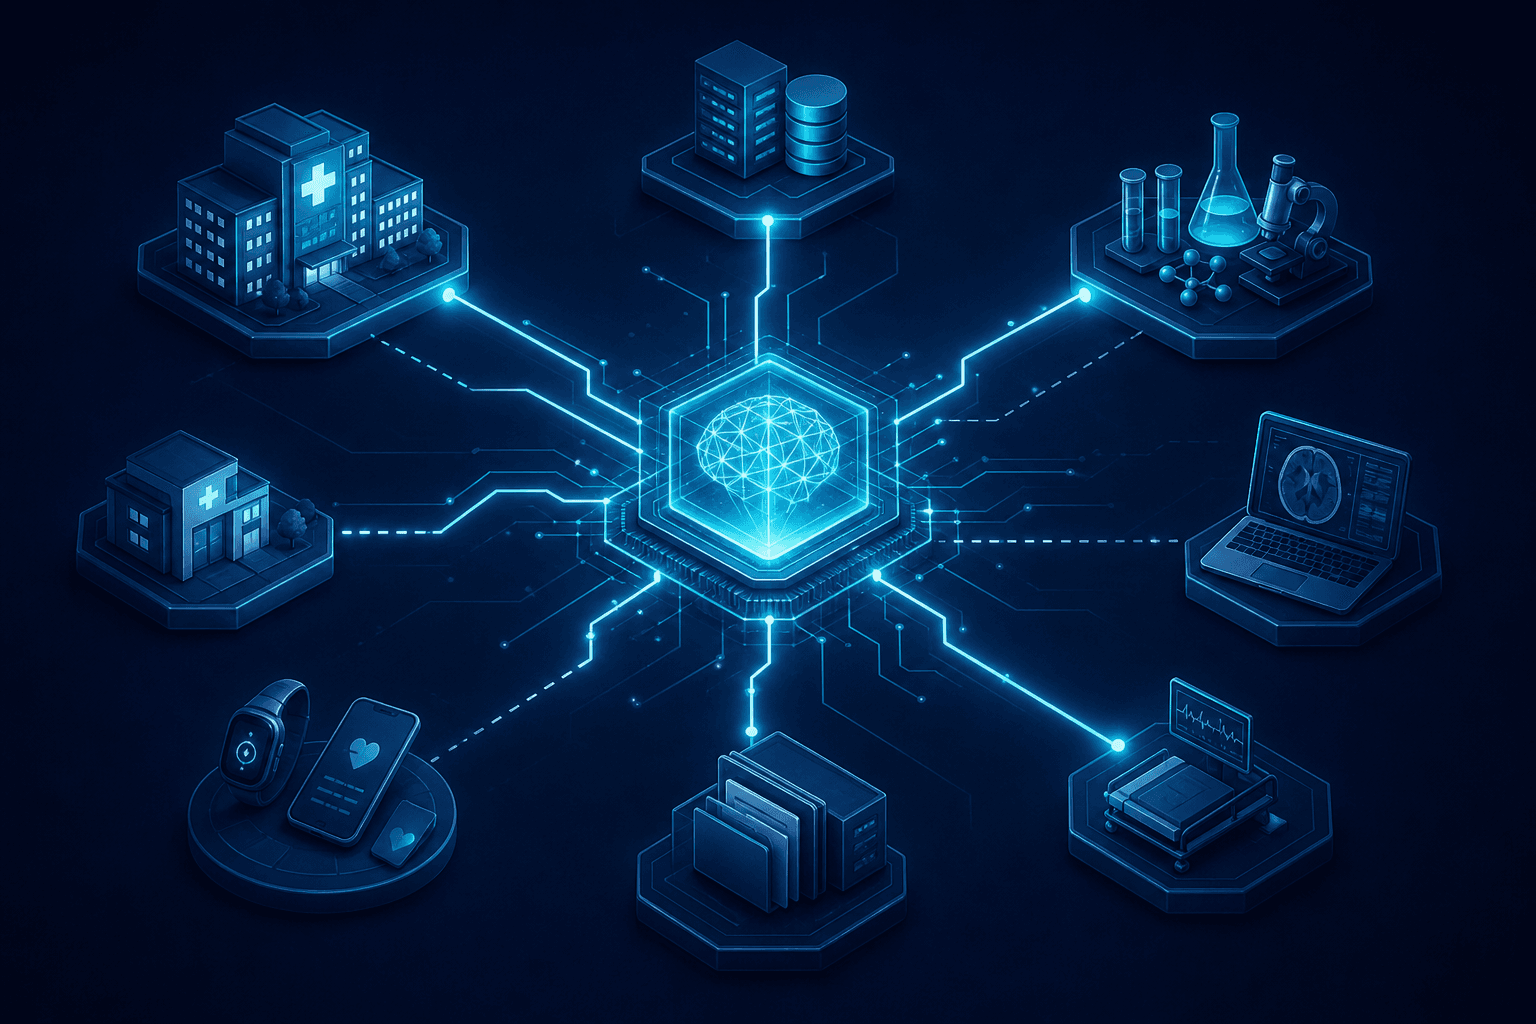
The read side gets most of the attention. A triage solution that lacks access to recent specialist notes is working blind on parts of the patient story it can't see. Missing context doesn't always trigger an obvious error. Sometimes it produces an answer that is plausible but clinically wrong for that specific patient.
The write side introduces a different category of problem. As soon as a workflow needs to close a care gap by scheduling a follow-up, update a medication reconciliation, or trigger a referral order, it needs write access. Write access is harder to negotiate, more tightly governed by EHR vendors, and carries higher compliance stakes than read access. That is why many AI deployments stall at the advisory layer instead of taking real actions.
In practice, a clinical AI deployment's reliability is determined by data access. A model that cannot reach the relevant clinical facts will produce outputs that are hard to defend, regardless of how capable the model itself is.
Semantic inconsistencies multiply the risk. A workflow ingesting lab results coded differently across two source systems may apply the same logic to values that don't mean the same thing. At foundational or structural interoperability, the data arrives. Whether the AI interprets it correctly depends on whether the semantic layer holds consistently across every data source in scope.
Read Access vs. Write Access: Why the Distinction Matters for AI
Read access is the easier half of the equation. FHIR APIs have made pulling patient data into an external application relatively straightforward, and most EHR vendors offer read-scoped connections as part of their standard integration offerings. An AI workflow can retrieve a medication list, a problem summary, or recent lab results without touching the source record.
Write access operates under a different set of rules. Placing a lab order, closing a referral loop, or pushing a finalized clinical note back into the EHR requires vendor-granted write scopes, often a separate credentialing process, and contractual terms that vary across Epic, Oracle Health, and Athenahealth. A bad write corrupts the authoritative record, and EHR vendors carry regulatory exposure for the integrity of certified data.
The practical consequence is that many AI deployments stay advisory. A workflow can surface a recommendation or generate a draft note, but a clinician has to act manually because the system lacks write permission to close the loop. For some use cases that is acceptable, but for others, like medication reconciliation after discharge or automated referral management, the advisory boundary is exactly where clinical value breaks down.
Write actions also require defined audit trails, role-based access controls, and clear attribution of who authorized the action, the same accountability questions covered in how Concurrence solves AI's trust crisis. The AI initiates the action, and a credentialed clinician or a configured rule set authorizes it. Building that accountability chain requires upfront work during integration scoping, not after deployment.
Semantic Interoperability: The Hardest Layer for AI to Work Through
Structural interoperability gets data from one system to another. Semantic interoperability determines whether the receiving system understands what arrived. For human clinicians, that gap is often invisible. A physician reading a discharge summary applies judgment to resolve ambiguous terminology and infer missing context. AI workflows don't have that fallback.
When a clinical AI solution ingests a lab result coded in LOINC from one source and a local proprietary code from another, the same logic may fire on inputs that don't mean the same thing, with no flag raised. Medication data makes this concrete: brand names, generic names, and formulary-specific codes for the same drug coexist across EHR implementations, so a contraindication check can miss an interaction because the medication arrived under an unrecognized code, a gap that motivated the Databricks partnership for Health World Models.
The 2024 systematic review in JMIR Medical Informatics on semantic interoperability of EHR systems found no single approach proving sufficient at scale. Shared vocabularies like SNOMED CT, LOINC, and RxNorm were built to solve this, but adoption is uneven and local extensions are common. Reaching consistent terminology across years of legacy data is a governance problem as much as a technical one.
For AI, the consequence is that semantic gaps propagate silently. A missing value may surface as an error, but a semantically inconsistent value looks fine.
How to Improve EHR Interoperability in Practice
No two institutions start from the same place, so there is no single prescribed path here. The approaches below are independent levers, and which ones matter most depends on where your current bottlenecks are.
- Adopt FHIR R4 APIs for new integrations. Where legacy HL7 v2 feeds exist and work, there is no need to replace them. New connections should default to FHIR R4, which is the basis for payer-facing APIs, patient access mandates, and the AI integration patterns now in widespread use.
- Connect to a TEFCA-aligned network. The CMS Interoperability Framework now lists CMS-Aligned Networks; early adopters reached general availability in July 2026, reducing the need for bilateral agreements with every external data partner.
- Audit vendor contracts for information blocking. Interface fees and restrictive API terms can make external data access economically unfeasible without technically violating the 21st Century Cures Act.
- Standardize on USCDI data elements for internal data models. Conforming to federally defined data classes reduces translation work when connecting to outside systems or deploying AI workflows that need consistent input formats.
- Invest in semantic governance before AI deployment. Map local code sets, lab units, and medication terminologies against SNOMED CT, LOINC, and RxNorm. This is the layer where AI outputs become unreliable when skipped.
- Use cloud-based integration layers to decouple AI workflows from EHR upgrade cycles, insulating deployments from vendor-side changes that would otherwise break them, a decision that often comes down to the broader build vs. buy question for healthcare AI infrastructure.
How Concurrence Approaches EHR Integration for AI-Powered Workflows
Every Concurrence deployment starts with a technical audit that maps read versus write constraints before any workflow is scoped. The gaps surfaced by that audit shape what an AI-powered workflow can actually do, and identifying them early avoids the common outcome of building something that stalls at the advisory layer because write access was never negotiated.
Native integrations with Epic, Oracle Health, and Athenahealth mean integration conversations do not start from scratch. The read versus write boundaries still exist, but they are known quantities with defined paths forward.
The Health World Model sits beneath every workflow, unifying data from EHRs, claims, and external sources into a single longitudinal patient view. A workflow assessing a care gap can draw on the full record context, beyond what the connected EHR exposes through its default API scopes.
Concurrence's AI-powered workflows can take real actions: scheduling, writing to the EHR, ordering labs, and messaging care team members, all from a single system instead of too many apps. Those write actions require the audit trail, role-based controls, and attribution chain configured during deployment. Before any workflow reaches a real patient, it goes through Digital Residency, Concurrence's simulation and evaluation engine, clearing a 100% safety pass rate across millions of simulated scenarios. To date, Concurrence has supported over 10 million patient interactions, and its published customer case studies report a 100% pass rate on clinical safety metrics, with 98% of interactions not requiring human escalation.
Final Thoughts on EHR Interoperability Standards and Barriers
The technical pieces of interoperability are largely solved. The harder work is semantic alignment, governance agreements, and write access, and those are organizational decisions as much as technical ones. Getting clear on where your data breaks down gives your AI deployments a much better foundation to build from.
FAQ
What does FHIR stand for in healthcare interoperability, and why does it matter for clinical AI?
FHIR stands for Fast Healthcare Interoperability Resources, an HL7-maintained standard for real-time data exchange via APIs. For clinical AI, it matters because FHIR R4 is the foundation for most current integration patterns, including payer-facing APIs, patient access mandates, and the read connections that give AI-powered workflows access to medication lists, lab results, and problem summaries without touching the source record.
Which healthcare AI platforms let agents write to the EHR or order labs, and what does that actually require?
Write access to EHRs like Epic, Oracle Health, and Athenahealth requires vendor-granted write scopes, a separate credentialing process, and contractual terms that vary by vendor. Most AI deployments stay at the advisory layer because write access was never negotiated during integration scoping. Concurrence's AI-powered workflows cover scheduling, lab orders, EHR documentation, and care team messaging, with audit trails and role-based controls configured before any workflow reaches a real patient.
How do EHR interoperability challenges affect clinical AI accuracy?
Semantic inconsistencies are the most dangerous failure mode: a workflow ingesting lab results coded in LOINC from one source and a local proprietary code from another may apply the same logic to values that don't mean the same thing, with no error flagged. A 2024 systematic review in JMIR Medical Informatics identified semantic interoperability as one of the primary unresolved challenges in EHR systems, with no single approach yet proving sufficient at scale. Mapping local code sets against SNOMED CT, LOINC, and RxNorm before deployment is the step most teams skip and most often regret.
What are the main barriers to EHR interoperability that health systems face in 2026?
The core barriers are vendor-specific data modeling, semantic inconsistencies across code sets and terminology, interface fees that make data access economically prohibitive for smaller institutions, and governance gaps where legal agreements for cross-organizational data exchange are absent even when the technical connection is possible. The OECD's 2026 health working paper confirms these barriers persist even in countries with mature EHR infrastructure. TEFCA was designed to close the governance gap, but adoption across care settings remains uneven.
What are the 2026 CMS Promoting Interoperability Program requirements, and how do they shape EHR investment decisions?
Eligible hospitals and critical access hospitals must submit electronic clinical quality measure data, complete required attestations, and earn a minimum total score within CMS collection timelines for the 2026 reporting year. Failing to meet those requirements triggers a downward payment adjustment. That payment pressure shapes which EHR data exchange investments get funded and in what order, which is why compliance timelines often drive interoperability roadmaps more than clinical need does.